Global warming, climate change, all these things are just a dream come true for politicians. I deal with evidence and not with frightening computer models because the seeker after truth does not put his faith in any consensus. The road to the truth is long and hard, but this is the road we must follow. People who describe the unprecedented comfort and ease of modern life as a climate disaster, in my opinion have no idea what a real problem is.
The previously blacked out secret contracts between Pfizer and the EU have finally been leaked and, as expected, the content is scandalous. We already know that we haven’t always gotten the truth from the government about Corona in recent years. The Pfizer leaks are now just another gust of wind toppling the house of cards of lies.
Pfizer warned the EU that its mRNA vaccine had been “rapidly developed” and that its side effects were “unknown”. Yet, the EU went ahead and sold it to the European public as “safe and effective” anyway.
In his latest YouTube video, already with 200,000 views, bestselling German author Marc Friedrich reports how the recently leaked mRNA vaccine MANUFACTUURING AND SUPPLY AGREEMENT between Pfizer and the EU show that the EU grossly misled its own citizens”.
The claim that the Pfizer and Biontech vaccines were “safe and effective” was totally made up by the EU.
“Rapidly developed”, unknown adverse effects
On page 48 of the Manufacturing and Supply Agreement – which had been kept hidden from the public – Pfizer warned Europe that its “Vaccine” had been “being rapidly developed” and that it would be up to the EU Member States to study the vaccine effects once provided:
Excerpt, page 48 of the Manufacturing and Supply Agreementwith the EU.
The text continues on the next page, where Pfizer explicitly warned that as a result, “the long-term effects are not currently known” and that it was not known if the “Vaccine” would have any “adverse effects”.
Excerpt, Manufacturing and Supply Agreementwith the EU.
Marc Friedrich calls the whole affair a huge scandal and “a pandemic of lies”. The manufacturing and supply agreement made with the EU is similar to the one between Pfizer and South Africa, which also was leaked to the public. The Purchaser (South Africa) “acknowledges that the long-term effects and efficacy of the Vaccine are not currently known.”
Excerpt, Supply Agreement with South Africa
The question now arises: If Pfizer did not know how safe and effective the vaccine was, and told the EU it was impossible to know, then why did the EU go ahead tell the public it was safe and effective? There was no way of knowing.
Malicious
This is nothing too difficult to understand. Imagine Boeing warning airlines that it’s new plane had been “rapidly developed” and so it was unknown if the plane would stay intact in midflight. At the same time regulators would simply give it the green light, and then tell the public the plane was safe and people should have no worries boarding it. Even worse, the government and employers would even mandate flying in it.
Later, after crashing multiple times, government regulators would then not keep safety statistics and just claim that the events were “extremely rare” and that overall the product rendered more good than harm. The shoddy planes would also be used in place of all other transport.
It’s little wonder that governments around the world are in no hurry to investigate the millions of COVID vaccine deaths and injuries. You can’t expect the guilty to prosecute themselves.
Three labs confirm fragments of DNA from manufacturing are left in the mRNA vaccines
We injected 70% of the world’s population with a barely tested admixture that included random lengths of DNA. We don’t know for sure if that DNA has been inserted into our nuclear DNA, but we’re not really looking either. The government just says mRNA can’t change your DNA. But could contaminated mRNA which is packaged in lipid nanoparticles, with gene therapy vectors and enhancers do that? Maybe, but whatever you do, don’t run those tests, right?
Are we changing germline genetics of the human race — getting into sperm or egg cells? We don’t know. These are just the games we play these days. We could easily have run those tests on sperm at least, before we approved anything in young fertile adults and children, but we didn’t. A Chinese scientist that did that once in a different experiment ended up in jail. Some researchers are quite concerned to put it mildly. The odds may be low, but the numbers are astronomical. After a few billion hands of poker everyone has a Royal Flush.
In March, Kevin McKernan, a molecular biologist, found DNA contamination in Pfizer’s mRNA Covid vaccines and published this in here and here. As soon as Kevin McKernan put out his paper on the presence of small fragments of SV40, the Factcheckers arrived to flood the scene with strawmen — declaring there’s no SV40 virus in vaccines — which is true, but no one said there was.
Now the presence of remnant DNA has been confirmed by two independent labs (Dr. Sin Lee and Philip Buckhaults) — so it wasn’t a freak finding or a mistake. It really is that bad. Indeed, Phillip Buckhaults set out to show the fears were overblown but instead, in astonishment, confirmed what McKernan found.
“My plan was to examine the vaccine to debunk the fear of SV40 being in the vaccine. … I checked them first by a PCR assay that uses primers against the vector, and lo and behold, it fired very hot. A very, very high signal. … and son of the gun, Kevin McKernan was right, this plasmid is present in the vaccine. I proved that there is NOT SV40 full virus, but there is plasmid DNA. And that plasmid does have a little piece of SV40 in it. “
A plasmid is a circle of DNA that’s a regular lab tool. In this case it contains about 10% of the SV40 virus, a virus that contaminated some polio vaccines around 1960, and has been the subject of many studies since. We find it in cancer cells, but did it cause the cancers? Academic opinion is divided (see the papers here). But the part of SV40 that’s in the plasmid is a potent part that amplifies or promotes whatever code follows it. Indeed, SV40 is used in gene therapy research — it makes a good vector. It’s such a good gene therapy tool that the residual DNA contaminant ought to be classified under gene therapy regulations instead of vaccination rules, says McKernan. He points out that there is an ongoing lawsuit in Australia with the TGA about this very issue.
The mRNA vaccines are an incredibly complex chemical product — easy to screw up
Creating mRNA vaccines was a monumentally ambitious chemical task. It’s no wonder things went wrong. An mRNA molecule is a chain of four different small molecules that is 4,284 bases long, in an exact sequence in the correct order. Effectively, on a molecular scale, we must connect these 4,284 nucleic acid bases in a row, and then wrap them in a fat layer (called a lipid nanoparticle). McKernan estimates each vaccination dose contains 13 to 40 trillion copies of the mRNA. This is not like the complexity of chemistry, say, used in creating ammonia in the Haber Bosch process, but something leagues, astronomical magnitudes beyond that. It is only possible because a billion years of evolution has crafted nano-scale machines that do a lot of it for us. We are merely co-opting the tools of biology. Grinding out thousands of bases is something even bacteria can do, but cleaning it up, that’s much harder.
To create all the copies of mRNA, and package it up, we use E.Coli — a bacterium — to be the molecular factory, then we have to strip out those factories, to disassemble them and all their “body parts” and remove them, without damaging the product, and in some batches we failed miserably.
Once again, we all hope friends, families and readers here, of course, got the good batches. It was a lottery.
Kevin McKernan Talks COVID Vaccine DNA Contamination, the Monkey Virus SV40 Promoter, and What’s Actually in the Vaccines
… many years ago there was a case where Dr. He in China did some genome edits on two babies. He made two CRISPR [clustered regularly interspersed short palindromic repeats] babies. That guy went to jail. Fast-forward to today, we’re willing to take that risk on billions of people. Now granted, CRISPR is a lot more effective, and doing it on germline is obviously going to affect every cell in the kid’s body. We’re probably not going to get every cell in the kid’s body when we inject them with one of these vaccines.
But if we hit a stem cell or if we hit a germline cell with a vaccine and we get an integration event, it’s effectively what that guy did, and it put him in jail. The ethical decay that’s occurred in the last five years in the biomedical community is absolutely astonishing. I can only attribute that to the vast amount of money that’s on the table for these vaccines.
What we do know is there is residual DNA in both shots, and this DNA is either right above the regulatory limit or tenfold higher. Our data has shown it to be tenfold higher than the FDA’s standards.
Why did we need such high doses? “… an RNA molecule for every single cell in your body.”
The RNA is just supposed to make enough protein to teach some white blood cells, not to teach every single damn cell in your body:
But what I think was perhaps a valid critique of their effort is that they never really knew how much you needed. Their dosage study looked at three doses. Why are we injecting 40 trillion of these things into people? Why does the immune system need such a huge payload to build an immune response? … we’re putting in truckloads of this material. We’re doing it over and over and over again, and it’s not working. These are all signs that something is horribly wrong. There’s 30 trillion cells in your body, so there’s more than an RNA molecule for every single cell in your body.
Would you like factory DNA in your ovaries?
We know from the biodistribution study that some of these LNPs are getting to the ovaries, so that’s a huge concern. If 1 percent of these LNPs get to the ovaries, there’s 40 billion in each shot, we’re getting down to 400 million that go to the ovaries. Now you’re starting to really concern yourself. If there’s only 300,000 oocytes in each female, and there are 400 million LNPs down there, these numbers are worrisome. What are we doing to the germline in the future generation?
(These numbers didn’t quite tally. Some studies estimate each LNP ball has on average 5 mRNA’s. So 40 billion LNP’s won’t carry 40 Trillion mRNA’s, as McKernan stated above. Perhaps the transcription tool “misheard”, or a reader can explain — either way, the important point stands. Human eggs are precious things, a million or a billion accidents either way is awful).
We don’t know where the vaccines went in body tissues:
This would seem the most basic first step, but we didn’t even do it properly.
Mr. McKernan: There were a lot of things they told us were impossible, which turned out not to be true. I would like to see more biodistribution studies. The biodistribution studies were not run with the mRNA that’s being injected. They ran it with a mock mRNA known as a luciferase mRNA that doesn’t necessarily give you the best signal to detect this over long periods of time.
They also ran those biodistribution studies over very short time windows. Of course, now we’re seeing mRNA in people’s plasma 28 days later, and we’re seeing it in breast milk. We’re seeing the spike protein in monocytes four months later. The biodistribution studies really didn’t track this long enough to know where it goes and for how long.
A cocktail of contaminants
The contaminants include not just a part of a monkey virus, but also antibiotic resistance, and also something called a 72 ACE pair enhancer which is apparently good for moving DNA into the nucleus (Oh no).
Mr. Jekielek: Let’s talk about what we know concretely. Please explain why you might have this SV40 promoter and enhancer in there in the first place.
Mr. McKernan: It’s a common tool used in the biotech industry to drive very aggressive expression of a gene. In this case, Pfizer has it in front of a neomycin resistance gene, which drives resistance for neomycin. The reason they want it there is so that they can grow this plasmid in E.coli. E.coli doubles every 30 minutes, so you can grow E.coli overnight and get gobs of this DNA. You then have to purify it from E.coli to make RNA out of it.
Fragments of DNA — especially ones packaged the right way — could integrate into our own genetic code. They may do nothing or everything depending on where they “land” in our 3.2 billion base genome. They may cause cancer if they land inside a key gene that usually protects us against cancer.
The concern is if this DNA integrates the genome, one portion of the SSV40 sequence is an SV40 promoter, a very strong promoter, which means it drives transcription wherever it lands in the genome. If this happens to drop itself in front of a proto-oncogene and drives a lot of expression off of a gene that’s known, if you hyper-express it and turn the cell cancerous, then we have a concern that DNA is in fact doing that.
Normally it’s difficult for loose bits of DNA to get near the nucleus of our cells where our DNA is kelp. But if the DNA is packaged up and has the right equipment, it can get there:
There are two concerns. There are promoters in this vaccine from SV40 and there’s an 72 ACE pair enhancer, which David Dean has shown is a very potent tool for moving DNA into the nucleus, and they’re right next to each other. If this DNA moves into the nucleus and it drags a promoter with it, and that integrates in front of a gene, it can disrupt gene regulation and potentially lead to the oncogenesis.
Pfizer hid the SV40 component from the EMA
This is a really bad look:
The really crushing thing here is Pfizer never disclosed the SV40 information to the EMA [European Medicines Agency]. They gave them a plasmid map of what the plasmid consisted of, with all of the features labeled, with the exception of the SV40 site.
They did that because they know the SV40 region is a very controversial base in its history in the vaccine field. The polio vaccines were contaminated with the full virus, not just these little components, but the full virus. The full virus has over 5,000 bases. The components we have are about 466 bases of the virus, but they’re arguably the most functional aspects of the virus’s genome for replicating and for gene expression.
The fact that they hid that this is in there from the EMA is a concern. We know from David Dean’s work that it’s used as a gene therapy tool, so it would clearly classify the residual DNA in the vaccines under the gene therapy regulations that we have in many jurisdictions.
Fragments of DNA that integrate may do nothing or everything depending on where they “land” in our 3.2 billion base genome. They may cause cancer if they land inside a key gene that usually protects us against cancer. All our cells have multiple layers of protection against cancer, but this may wipe one of them out.
Stop vaccines for children and adults of fertile ages until we know
If the DNA of eggs and sperm is being changed — it may mean the death of that particular embryo, which may delay pregnancy but not preclude it. It could translate into falling fertility rates, or it may mean children born with a higher risk of disease or disability. We may be playing “shotgun” genetics with the next generation. Why aren’t our Ministers of Health looking? It would be easy to analyze sperm samples and answer this question. It’s a lot harder to test eggs. It’s the sort of test that could be done in weeks.
Now that the DNA contamination is known, the question of culpability and informed consent gets so much more pointed. But for our regulatory agencies — the question remains — why didn’t test for this at the start of 2021?
What kills much faster than cancer? — “endotoxins”
McKernan admits that bacterial endotoxin contamination scares him more than the DNA — at least in an immediate sense. The remnant shells of the bacteria — the body parts of E.Coli — are called lipopolysaccaride, or LPS, and they are highly allergenic. We deal with small doses of this all the time, but in large doses, they can cause anaphylaxis — the potentially deadly overactivation of our immune systems. Just this contaminant alone may have caused sudden deaths within minutes of injection.
There is some risk that if you don’t fully purify it from E.coli, you can leave behind what’s known as endotoxin or lipopolysaccharides, usually abbreviated as LPS. This is an additional risk that Pfizer took on. Moderna’s doing a very similar thing, although they don’t have SV40 in there. They are using E.coli to amplify their plasmid DNA, and it comes with some of this risk.
The good news is that if the endotoxins didn’t kill you, at least that risk is gone, unless you have a booster.
Cherry picking the tests to pass outdated regulations
The European Medicines Agency (EMA) sets a safe ratio of RNA to DNA (well, they say it’s safe), but the pharmaceutical companies cherry picked the type of tests they used, so as to overestimate one and underestimate the others and “pass”. How much do any of them care about your health?
The EMA has a different standard that’s a ratio metric standard. When looking at RNA to DNA ratios, it’s even worse. The actual outcome is that there is more like a 17 to 80-fold gap from what is required in the regulations, as best we can tell.
I’ve only seen Pfizer’s documentation on this, but when they are measuring this and giving data to the regulators, they’re using two different tools to measure the RNA versus the DNA. That’s a mechanism for them to cook the books here. They shouldn’t do that. There’s tools like qPCR that can measure both DNA and RNA, but instead they’re measuring the RNA with fluorescence like a qubit or a fluorometer, and they’re measuring the DNA with qPCR. That inflates the amount of RNA they get and depresses the amount of DNA they get so that they can squeak through these regulatory requirements without anyone really understanding what’s going on.
Coding for the nerds
Lastly, this, below, is just a part of the code for the plasmid DNA contaminants in the mRNA vaccine. Click to enlarge. The A, C, T and G stand for molecules called adenine, cytosine, thymine and guanine. Think of this as the C++, or Python of biology. Given the current state of play, perhaps it’s worth becoming a bit more familiar with molecular biology.
It is double stranded — and in the alternate chain, which is effectively a back up “mirror” copy, we see C always pairs opposite G and T always sits opposite A. This is exactly the same as our DNA — same bases, same language. Our cellular machinery will potentially engage and read this code and produce the products — whatever they are.
—————————————————
hat tip: John Connor II, Leo G, Konrad, Ian B, bella.
Kevin McKernan1*, Anthony M. Kyriakopoulos2 and Peter A. McCullough3 (2023) Differences in Vaccine and SARS-CoV-2 Replication Derived mRNA: Implications for Cell Biology and Future Disease, Submitted for peer review. [DocX] (page 11)
A recent court order requiring disclosure of the South African COVID-19 vaccine procurement contracts has caused a stir in social media and raised hopes that some of the secret clauses offering special protection to manufacturers might finally be revealed.
A recent court order requiring disclosure of the South African COVID-19 vaccine procurement contracts has caused a stir in social media and raised hopes that some of the secret clauses offering special protection to manufacturers might finally be revealed. The Romanian Member of the European Parliament Cristian Terhes, who has long criticised Ursula von der Leyen and the EU Commission for publishing heavily redacted versions of the EU’s own procurement contracts, hailed the ruling in a tweet as a “huge win for transparency and accountability”, pointing, in particular, to the inclusion of the all-important ‘Pfizer’ contract among the documents to be released.
But why the excitement? The EU’s own procurement contract or Advanced Purchase Agreement (APA) with the consortium of Pfizer and the German company BioNTech has been available online in unredacted form for well over two years now: since, more precisely, April 2021, just shortly after vaccine rollout. It does indeed contain hair-raising clauses, which would undoubtedly have provoked massive opposition and ‘vaccine hesitancy’ had they been more widely known.
Consider, for instance, the following clause from Article 1, paragraph 4, of the Vaccine Order Form which is appended to the APA: “The Participating Member State further acknowledges that the long-term effects and efficacy of the Vaccine are not currently known and that there may be adverse effects of the Vaccine that are not currently known.” (See full paragraph below.) How many Europeans would have rushed to take the vaccine or even consented to take it if they had known that?
But they did not know it. For here is what the same paragraph looks like in the redacted version of the APA posted by the European Commission.
This ‘acknowledgement’ clause in the order form – acknowledgement, in effect, that the manufacturers knew neither if the vaccine was safe nor if it was effective, at any rate in the long-term – is in addition to the clauses which already provide the manufacturers extremely wide-reaching indemnification in the section on indemnification of the contract proper. See, for instance, the excerpt from Article I.12.1 below.
The ‘contractor’, as specified on the first page of the APA, refers to Pfizer and BioNTech collectively.
This is how the same passage looks in the redacted version of the contract posted by the European Commission.
Here is what the full page looks like.
And the following page.
In fact, apart from the first sentence, the entire section on indemnification, covering nearly three full pages of text has been redacted in the version of the APA posted by the Commission (see pages 24-26).
It is these extensive redactions which have been the focus of Cristian Terhes and other vaccine-critical members of the European Parliament. Taking Ursula von der Leyen and the Commission to task for their lack of transparency, Terhes has made a regular practice of theatrically holding up blacked-out pages of the contract in plenary sessions. (See here, for instance, from October 2022.)
But if the unredacted version was available anyway, why did Terhes and his colleagues not also refer to that, i.e., to the actual content of the passages which were being hidden? And how did the unredacted APA and the obviously explosive provisions it contains fail to become better known?
Well, Cristian Terhes and the other MEPs will have to answer the first question themselves. If they were unaware of the availability of the unredacted document, they were made aware of it in September 2022, namely, by the present author in a tweet-reply to Cristian Terhes to which Terhes replied in turn.
But the answer to the latter question – why the existence of the unredacted APA has not become better known – is perhaps more intriguing and would appear to have something to do with the form of stealth censorship or ‘visibility filtering’ which has since become the norm precisely on Twitter.
Thus, in July 2022, after stumbling upon the unredacted contract, I posted a thread on it on Twitter, which quickly went somewhat viral by the standards of a small account, garnering hundreds of retweets and likes and eventually, according to Twitter’s own metrics, just over 100,000 impressions. I began the thread with the same acknowledgement of the unknown efficacy and safety of the vaccine highlighted above.
On September 11th 2022, I quoted this thread in the above-mentioned tweet-reply to Cristian Terhes and asked him why he was showing redacted copies of the EU contracts when the unredacted documents were available. Terhes’s response was to call into question the authenticity of the unredacted document. “Nobody can confirm that those unredacted versions are the real one,” he wrote.
But the Pfizer-BioNTech contract was not just mysteriously floating around the web and it was not published by any obscure conspiracy website. It was published rather by the Italian public broadcaster RAI. The RAI is the Italian equivalent of the BBC.
The Pfizer-BioNTech contract has been available ever since on the RAI server. (Beware that when I first tweeted the contract in July 2022, it temporarily became unavailable, perhaps because the resulting traffic was greater than the server could handle.)
Furthermore, four days after publication of the RAI article, on April 21st, the Spanish daily La Vanguardia, Spain’s third largest newspaper in terms of readership, also announced that it had come into possession of the unredacted Pfizer-BioNTech contract – presumably simply by downloading it from the RAI website! – and published an article titled ‘The Contract With the European Commission Absolves Pfizer of Liability’.
Although, unlike the RAI, La Vanguardia did not post the contract as such, it did publish photos of selected pages, including a photo of the first page of the indemnification section I highlighted above, which it likewise contrasted to the redacted version published by the Commission.
On that same day, none other than Reuters also published an article on the leaked contract, citing La Vanguardia’s scoop (even though the scoop was in fact the RAI’s). Reuters, however, discreetly avoided mentioning the issue of indemnification, merely focusing on the price of the vaccine. (See ‘Leaked EU-Pfizer contract shows price for COVID vaccines set at 15.5 euros per dose’.)
So for three major European media, the RAI, La Vanguardia and Reuters, there was no question about the authenticity of the document when it first emerged in April 2021 – and before it again fell into oblivion. In the meanwhile, incidentally, Norman Fenton has also come upon the above-cited order form from the APA via a Slovenian FOI request, thus providing further confirmation of the document’s authenticity, supposing it were really needed.
But what was especially curious about my Twitter interaction with Cristian Terhes is what happened after it. Almost immediately after flagging the unredacted APA in reply to Cristian Terhes’s tweet, my Twitter account was hit with a shadow ban. This was what the results of my shadowban test looked like on the next day.
At the time, under the old Twitter regime, being shadow-banned was still a kind of status, which could be easily and accurately verified by online shadow-ban tests (or even by users themselves by searching for their own tweets when logged out of their accounts).
Furthermore, some other Twitter users let me know that they were unable to like or retweet my reply. See below, for instance. Similar feedback in the same vein is no longer available since Twitter has permanently suspended the author’s account.
This was not all that unusual per se. It will be recalled that tweets labelled ‘misleading’ under the old regime could not be liked or retweeted. But what was ‘misleading’ about my tweet? And, more to the point, it was precisely not labelled as such. Nonetheless, it appeared – surreptitiously – to be subject to similar sorts of restrictions.
Thereafter, engagement with my reply-tweets quoting the thread plummeted in general, occasionally popping up again, but still to less than half the previous level, before trending down to essentially, and apparently permanently, non-existent under the new Twitter regime. The below graph of relevant engagement (likes plus retweets) before and after the date of the interaction with Terhes illustrates this. It only includes tweets in which I used the word ‘unredacted’.
Restricting engagement remains very much a thing on the new Twitter/X, as X CEO Linda Yaccarino readily admits and as can be seen in the below extract on ‘tweet-level enforcement’ from the X ‘Help Centre’. Indeed, the actions taken to suppress tweet visibility appear to be more extensive now than under the old regime. (‘misleading’ tweets could be quoted, for instance.)
But unlike the old Twitter, which as a rule let users know when action was being taken against a given tweet, ‘X’ no longer publicises the fact.
Interestingly, the ‘Help Centre’ also acknowledges that such action may be taken in response to a “valid legal request from an authorised entity in a given country”. Who knows what a “valid legal request” is. But presumably the European Commission would count as such an “authorised entity” – especially since the Commission is designated as the ultimate regulator of online speech under the EU’s Digital Services Act. (See, for instance, here, here and here.)
In any case, the party with the most obvious interest in suppressing the unredacted APA is, of course, the party that redacted the document in the first place: the European Commission. It is not hard to imagine why the Commission would want, so to say, to ‘re-hide’ it.
Did old Twitter restrict the visibility of the unredacted APA in response to a request from EU authorities? Is new Twitter/X continuing to do so today?
Robert Kogon is the pen name of a widely-published journalist covering European affairs. Subscribe to his Substack and follow him on Twitter.
Moderna and BioNTech shares both fell to their lowest price in years on Monday as the companies behind the most widely-used mRNA COVID-19 vaccines grapple with investor disappointment with crashing revenues.
COVID-19 vaccine and syringe sitting over blue financial graph background. Selective focus. Horizontal composition with copy space. COVID-19 Vaccine and Stock market and finance concept.
Moderna and BioNTech shares both fell to their lowest price in years on Monday as the companies behind the most widely-used mRNA COVID-19 vaccines grapple with investor disappointment with crashing revenues. Forbes has the key points:
BioNTech and Moderna’s stocks fell 8% and 6%, respectively, a decline spurred by BioNTech’s earnings report revealing the German firm’s sales fell 95% year-over-year last quarter.
Moderna’s fresh decline came after it reported a 93% annual decline in quarterly revenues in its own earnings release Thursday.
Moderna’s $101.20 close Monday was its lowest since November 2020, while BioNTech’s $98.50 close was its lowest since March 2021.
BioNTech, which developed a Covid vaccine with Pfizer, said Monday it expects to generate $5.5 billion in Covid vaccine sales this year, a 70% decline from 2022, while Moderna’s $6 billion to $8 billion in forecasted Covid jab sales is similarly about two-thirds below its $18 billion of revenue in the unit last year.
The stock crashes moved against broader market gains, with the Dow Jones Industrial Average’s 408-point, or 1.2%, rally its strongest since June 2nd.
It couldn’t have happened to a nicer bunch of medical billionaires.
Investors are voting on the failure of mRNA technology with their feet, fleeing the stocks of Moderna and BioNTech, the two companies that had the greatest wins on the mRNA Covid jabs.
In 2021 and 2022, Moderna and BioNTech rode Covid to tens of billions of dollars in profits. That gravy train is over.
Today, shares in Moderna and BioNTech fell below $100 a share for the first time since the jabs came to market in 2020, plunging almost 10% after BioNTech reported weak second-quarter sales and said it would reduce its planned research spending.
Both companies are down almost 80% from their 2021 peaks. Pfizer, which markets BioNTech’s mRNA jab and shares profits equally with BioNTech, has also fallen, though not as much, since Pfizer has non-mRNA products.
Behind the plunge: demand for Covid shots has fallen off a cliff worldwide and shows no signs of recovering. Last month, Germany said it expected to throw out 200 million expired shots, more than the total number it has administered.
A few months ago, Pfizer predicted that 100 million Covid jabs would be administered in the United States in 2023. Pfizer’s executives no doubt expected that estimate was conservative, given that publicly traded companies would much rather surprise investors with good news than bad news.
But Pfizer disclosed last week that only about 12 million shots have been given so far – and most came very early in the year. “The 12.4 million doses are behind our earlier projections,” Pfizer Chief Executive Albert Bourla acknowledged on a conference call last week. (Full disclosure: I am suing Bourla as part of Berenson v. Biden.)
Meanwhile, efforts to expand mRNA technology to jabs to prevent the flu and RSV are faltering. Large clinical trials suggest that the mRNA shots for those illnesses cause serious side effects at the same rate as they do for Covid.
Meanwhile, the Telegraph reports that NHS flu jabs and Covid boosters will be axed for adults under 65 this winter as the health service attempts to “go back to normal”.
The Government’s Joint Committee on Vaccination and Immunisation is expected to set out plans on Tuesday which will mean 12 million people aged 50 to 64 are no longer eligible for free vaccines.
The rollout is also expected to start later than normal for those who are given jabs, with the drive not set to begin until October.
The vaccination drive usually starts in early September in an attempt to ensure sufficient protection against an early flu season.
Health officials said the later start would ensure that the vulnerable are protected in the depths of winter when viruses are most likely to spread.
Is that an admission of very short efficacy, if they have to give it in October to ensure it still works in December? Looks like it.
Detected fraudulence aside, there is no stronger criticism of a study than refuting the key result by using the study data. That opportunity does not arise often.
Detected fraudulence aside, there is no stronger criticism of a study than refuting the key result by using the study data. That opportunity does not arise often.
I present a striking example, pertaining to a study from Israel. Trying to be methodical, my article is somewhat on the long side, but the implications at the end are radical and broad.
Goldin et al. estimated the effectiveness of the Pfizer vaccine on several Covid-related outcomes, including death, in residents of long-term care facilities in Israel (mean age of 83 years). The large cohort (over 43,000) was heavily skewed towards vaccinated residents (90%). Only about 4,000 residents were not vaccinated.
Using a statistical method called survival analysis, the authors reported two age-adjusted values of vaccine effectiveness (VE) against Covid-related death:
Skipping 10 days after the first dose, VE was 72%.
Skipping about seven days after the second dose, VE was 85%.
Goldin et al. also analysed all-cause death as an endpoint, which many researchers have omitted. Most important, two of their figures (below) show the cumulative number of Covid deaths and all deaths at several time points — from which we can compute the cumulative number of non-Covid deaths. The latter data have been consistently hidden in studies of vaccine effectiveness.
Moreover, the studies provide mortality data, not just with the seven- or 10- day gaps, but since an ‘index date’ – the date on which the first dose was injected. We can thus analyse the data the way they should have been analysed – no skipping.
Fig. 2 COVID-19-related death. Source: Goldin et al.
For some reason, the time points in the table for Covid death do not exactly match the time points for all deaths, but they are not too far apart (figures above). Therefore, the number of Covid deaths at the time points for all-cause death (30 days, 60 days, etc.) can be reasonably estimated by interpolation (examining the height of the line at 30 days etc.) Then, subtracting the number of Covid deaths from all-cause deaths reveals a crucial piece of data: the number of non-Covid deaths.
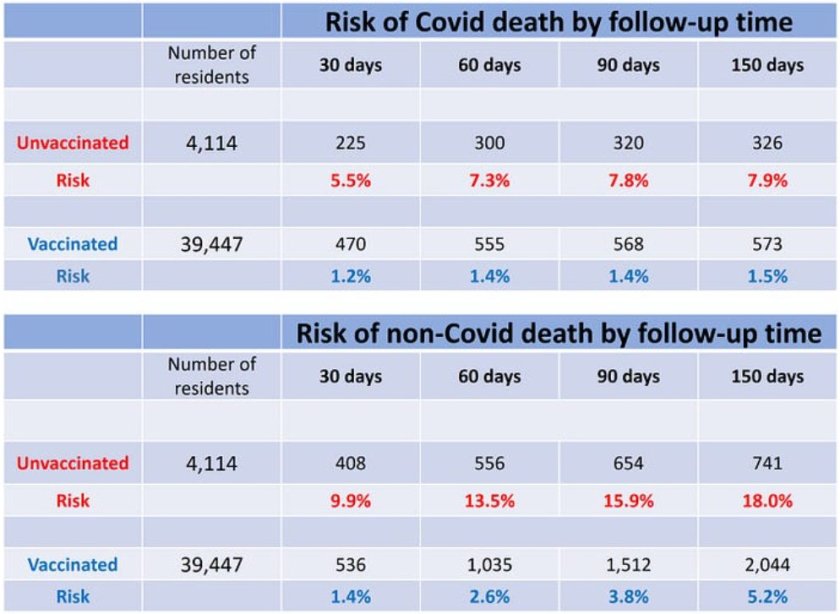
My busy tables below show the cumulative number of deaths (Covid, non-Covid) in vaccinated residents and unvaccinated residents by the end of the follow-up (five months) and by three interim time points (after one, two and three months). Using simple analysis, formally called ‘cumulative incidence’, I computed the risk of the two types of death in vaccinated (blue) and unvaccinated (red) residents.
The top table shows that the risk of Covid death was consistently higher in unvaccinated than in vaccinated – a positive ‘vaccine effect’ – but the surprising result is revealed in the bottom table: that was also the case for non-Covid death! The mortality rate from non-Covid causes in 4,114 unvaccinated residents of nursing homes in Israel was three to seven times the mortality rate in their vaccinated counterparts, depending on the follow-up time. Or vice versa — the mortality rate from non-Covid causes was substantially lower in nursing home residents who were vaccinated against Covid. That astonishing result is seen early on, within one month of the first dose.
Does the Pfizer vaccine protect against death from non-Covid causes?
We have yet to hear someone making the claim.
If not, what is the explanation?
It is simple and not astonishing at all. The decision of whom not to vaccinate was not random. It must have been based on reasonable medical considerations, particularly life expectancy. For instance, what is the merit of vaccinating a 90-year-old who suffers from advanced dementia and metastatic cancer?
Those 4,114 unvaccinated residents were sicker to begin with. Their life expectancy was shorter, regardless of possible SARS-CoV-2 infection, and that’s why their non-Covid mortality was several fold higher.
Stated differently, belonging to the unvaccinated group was a general marker of poorer health. Or vice versa — belonging to the vaccinated group was a marker of better health. That’s on average, of course.
The implication of the ‘healthy vaccinee’ phenomenon — when estimating vaccine effectiveness — is called confounding bias. A naïve comparison of Covid mortality in vaccinated people and unvaccinated people, even if age-adjusted, is grossly misleading because the latter have higher risk of death to begin with. At least part of their higher Covid mortality, if not all, has nothing to do with not being vaccinated. They are simply sicker people.
Even Goldin et al. are aware of the bias, to which they devote one sentence at the very end of the article: “The unvaccinated group might have suffered from more comorbidities, leading them to be more susceptible to SARS-CoV-2 infection and death, thus making the vaccine’s effectiveness seem higher than it actually is.”
Some researchers think that the bias operates in the opposite direction (called confounding-by-indication bias), whereby the unhealthy person is more likely to be vaccinated because he or she is at risk. Regardless, the net effect of the healthy vaccinee bias and confounding-by-indication bias, if the latter exists, is shown in the bottom table (above): those who were vaccinated had substantially lower non-Covid mortality. They must have been healthier, on average, not the other way around.
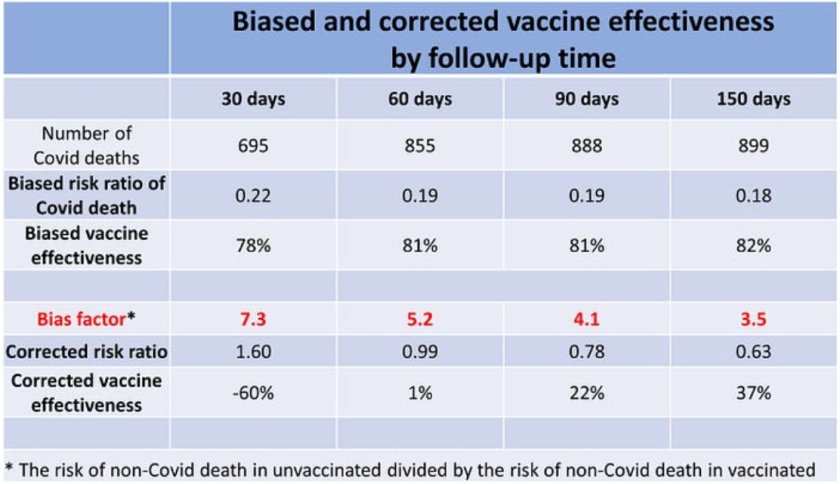
The table below shows the risk ratio and VE against Covid death, as computed from the data in the top table above. VE is around 80% when calculated at various time points, and my simplified computation for the entire follow-up (82%) is similar to the main result of Goldin et al. (85%). Recall that all these estimates are distorted (biased) versions of the truth due to the healthy vaccinee bias (and naïvely assuming no additional sources of bias).
Most important, the data on the risk of non-Covid death allow for rudimentary correction of these estimates, which is certainly better than no correction at all. The method is best explained by a simple example.
Suppose the apparent risk of Covid death is twice as high in unvaccinated than in vaccinated, which means a biased risk ratio of 0.5 in favor of the vaccinated (i.e., the vaccinated are half as likely to die as the unvaccinated), and thus a biased VE of 50%. But suppose we find out that the risk of death from non-Covid causes isalsotwice as high in unvaccinated. What does that imply?
Vaccination has made no difference. It had no effect on Covid death. A two-fold risk of Covid death is the expected, ‘baseline’ risk of death in unvaccinated because they are generally sicker. Vaccinated or not, they would have had a two-fold risk of death from Covid than their vaccinated counterparts — just like their two-fold risk of death from non-Covid causes. The biased risk ratio of 0.5 (VE of 50%) should be corrected to 1 (VE of 0%).
To get a risk ratio of 1, from a biased risk ratio of 0.5, we need to multiply 0.5 by 2; the number 2 here may be called the bias factor. The bias factor captures the underlying higher risk of death in those who were not vaccinated; in the example, the unvaccinated were twice as likely to die of non-Covid causes, so the bias factor is 2. It is estimated by the calculating the risk ratio of non-Covid mortality, comparing the unvaccinated to their vaccinated counterparts.
In my simple example, the correction method completely nullified the presumed effect of a vaccine, the bias factor of 2 cancelling out entirely the biased VE estimate of 0.5. As we’ll see next, the outcome could be anything from attenuated VE to negative VE, where a supposedly beneficial vaccine is actually harmful.
The table below shows the bias factor in the study of Goldin et al. by follow-up time, along with the corrected risk ratio and the corrected VE. For example, over the entire follow-up, unvaccinated residents of nursing homes in Israel were 3.5 times more likely to die from non-Covid causes than vaccinated residents – a bias factor of 3.5. Multiplying the biased risk ratio of 0.18 (the risk ratio is 1 minus the VE, in this case 82%) by 3.5 changed the risk ratio to 0.63 and thus reduced VE from 82% to 37% (i.e., 1 minus 0.63, as a percentage).
Almost all Covid deaths have accumulated by the third month (888 out of 899). Indeed, the biased VE estimate was essentially the same (81% vs 82%). Since the bias factor was higher at 4.1 (because non-Covid deaths in the unvaccinated were higher earlier on in the follow-up), the corrected VE is now 22% (multiply the 0.19 biased risk ratio by 4.1).
Whether VE was 22% or 37% — that’s a mediocre vaccine. And worse results are forthcoming.
The biased estimates of VE increased slightly over time (from 78% to 82%). The bias factor, however, decreased from 7.3 in the first month of follow-up to 3.5 over the entire follow-up, which is not too difficult to explain. Given the shorter life expectancy of the unvaccinated cohort, the most vulnerable members of that cohort died earlier. The remaining people gradually made up a somewhat ‘healthier’ surviving cohort, thereby narrowing the non-Covid mortality gap between unvaccinated and vaccinated.
By the end of the first month the bias factor was 7.3 and by the end of the second month it was 5.2, whereas the biased risk ratio was similar in each month. This works out as a harmful effect of the Pfizer vaccine in the first month (VE of minus-60%), and overall null effect by the end of the second month (1% VE). That’s negative and negligible VE, respectively, against Covid death.
When, as in this case, the inference strongly depends on the amount of data accumulated — no effectiveness by the second month versus 22% and then 37% effectiveness with longer follow-up — researchers have a rule of thumb: the inference is stronger where we have most of the data, not after adding a few more observations. About 95% of all Covid deaths have occurred in the first two months (first row in the table above). This suggests the zero VE estimate may be the truest.
The correction method is not perfect, and the result depends on the value of the bias factor (an estimate by itself). Nonetheless, an increased risk of Covid death during an early post-vaccination hazard period is compatible with other data. Indeed, news outlets in Israel reported outbreaks of Covid infection in nursing homes shortly after the initiation of the vaccination campaign.
Below is a translated excerpt from a news report, dated January 14th 2021, about three weeks into the campaign:
Once again, a failure in nursing homes: at the same time as the second dose of COVID-19 vaccines is being distributed, the pandemic is hitting hard in the institutions where the elderly live. In the past two weeks, outbreaks have been recorded in no fewer than 160 geriatric institutions, and 1,098 new confirmed cases have been detected among residents of institutions licensed by the Ministry of Health alone.
In parallel to the surge in the number of patients in nursing homes and assisted living centres, in the past two weeks ‘Senior Shield’ [a task force for Covid management in nursing homes] stopped publishing the daily report on Covid morbidity data in geriatric institutions on the Ministry of Health website.
Why did they stop reporting? Have they also seen a surge in Covid death of vaccinated residents of nursing homes during the first month of the campaign?
Whether the Pfizer vaccine had time-dependent negative effectiveness, no effectiveness or mediocre effectiveness, the excellent effectiveness against Covid death of 85%, as reported by Goldin et al., was false. Assuming this conclusion is not challenged, what are the implications?
Some readers might think that refutation of one study does not mean a lot. Goldin and colleagues are wrong, but there are other studies that support the narrative of a ‘highly effective vaccine’ in the vulnerable population – and we did not show that the results from those studies were also false.
That’s not how deductive inference works. If VE against Covid death is shown to be far from ‘highly effective’ in one study of the frail elderly, we must deduce that all other studies that reported similar or better VE are false as well — likewise distorted by the healthy vaccinee bias. Otherwise, we have to make an implausible assumption: that despite the severe bias we have uncovered in Goldin et al., the play of chance nonetheless miraculously generated for the authors the true VE that matches other, non-biased studies. Far more likely is that those other studies, in producing a high VE, are similarly confounded by the healthy vaccinee bias.
What should happen next?
First, the paper by Goldin et al. should be retracted.
Second, vaccination of the frail elderly with updated Covid vaccines should be halted.
Third, public health agencies should initiate a Request for Applications (RFA) for placebo-controlled randomised trials of Covid vaccines in nursing homes — with Covid and all-cause mortality as endpoints.
Such trials are scientifically justified because residents of nursing homes, the most vulnerable population, were excluded from the original trials (in which death was not an endpoint). Moreover, randomised trials in this unique population become ethically obligatory when corrected VE against Covid death from observational data ranges from mediocre to negative and there are known vaccine-related fatalities.
Dr. Eyal Shahar is Professor Emeritus of Public Health at the University of Arizona. This article first appeared on Medium.
A great many journalists, bureaucrats, politicians and ordinary people were complicit in the excesses of the past several years, and as the policies of the pandemic continue to sour, they’ll do anything but talk about it. This more than anything is the reason for the deafening silence surrounding all of these matters.
I know it’s not the repudiation we hoped for, but the widening displeasure over the deeply idiotic and imprudent contracts that the European Union negotiated with Pfizer and BioNTech for COVID-19 vaccine doses says a lot about where the vaccinators find themselves, politically and socially, at this late hour.
In Germany, by the end of March 2023, around 83 million COVID-19 vaccine doses expired and were thrown away by with the federal government alone. Health Minister Karl Lauterbach (SPD) has informed a private session of Bundestag budget committee of these developments …
These figures raise many questions. Did Germany, especially under Lauterbach’s predecessor Jens Spahn (CDU), but also during Lauterbach’s tenure during the fight against the pandemic, order too much vaccine? Could they have avoided these costs, which reach into the billions? Or did the state have no choice, because it was not foreseeable how many people would get vaccinated, and how many injections would be needed for effective protection in the longer run?
What devastating answers all of these questions have.
In any case, the EU and the Federal Republic of Germany have purchased far more vaccine than is needed now. As the Ministry of Health informed the Bundestag, Germany has donated 120 million vaccine doses to other countries. Even after these donated doses left the central warehouse, further doses nevertheless expired …
The Ministry explains that additional doses have expired “at the various stages” of the supply chain. This refers to doses shipped to wholesalers, pharmacies and doctors’ offices. These parties are in turn responsible for “proper disposal”, the ministry explains. They did not provide figures on how many doses had expired and been destroyed by these wholesalers, pharmacies and medical practices. It is possible that these numbers have not been collected.
In other words: The 83 million figure represents a floor; nobody actually knows or is all that eager to tabulate how many doses have been thrown away.
When asked by the SZ, the Ministry of Health did not say how much the expired and destroyed doses at the federal level cost. Publicly available data nevertheless supports the assumption that the costs to the taxpayer… are in the billions.
And that may not be all.
Through the start of 2023, the federal government had ordered a total of 672 million doses for 13.1 billion Euros, generally via the EU. Each jab therefore costs on average just under 20 Euros … According to the Ministry of Health, by the start of May, around 192 million doses had been injected in Germany, and some of the deliveries are still outstanding.
More than a year ago, the Berlin-based newspaper Tagesspiegel asked whether Lauterbach was threatened with “billions in damages”. At that time, it was already becoming apparent that vaccine could remain unused. In mid-2022, 3.9 million vaccine doses had expired. By the beginning of 2023, there were already 36.6 million vaccine doses. And now, only five months later, it is already 83 million. By the end of last year, approximately 54 million doses had expired and in the first quarter of 2023, approximately 29 million doses had been destroyed, the ministry informed the Bundestag.
Possibly even more vaccine will have to be destroyed. As of the beginning of May, the Federal Government still has stores amounting to around 120 million doses. Their future is “fraught with uncertainty” and depends, among other things, on the future course of the pandemic, the Ministry of Health informed the Bundestag. The Federal Government still intends to give “unneeded vaccine” to other countries.
Not a single country anywhere on earth can be found to take this stuff.
To avoid having to destroy more vaccine, the EU has now negotiated a partial cancellation of supply contracts with the pharmaceutical companies BioNTech and Pfizer. A “cancellation fee” is due for this, Lauterbach informed the Bundestag. According to reports, Lauterbach did not give a figure. The cancellation fees for unwanted vaccine is likely to reach costs in Germany alone of hundreds of millions of Euros.
While the details of the deal are officially secret, an outraged Polish health minister revealed several weeks ago that Pfizer and BioNTech have demanded that EU countries pay 50% of the cost for every previously ordered yet unneeded vaccine dose.
At the end of the article there lurks this foul paragraph:
With early access to safe and effective vaccines, many lives have been saved and millions of people have been protected from serious illness. The economic costs of the pandemic have also been reduced and the “impact on social life has been noticeably mitigated”. The vaccine surplus is a consequence of this strategy. This is how the Ministry of Health justified the bulk purchases in the Bundestag.
We’ve been over this many times at the plague chronicle, but as long as politicians and the press continue to indulge in these hollow excuses, I’ll keep repeating myself: It’s strange indeed that enthusiasm for these SaFE aNd EfFeCtIvE vaccines should have plummeted in precise inverse correlation to public experience with them. You’d almost think that the more the vaccinators were allowed to vaccinate, the more everybody decided the vaccines weren’t for them after all. This is hardly the response you’d expect to such miraculous, life-saving, side effect-free products.
A great many journalists, bureaucrats, politicians and ordinary people were complicit in the excesses of the past several years, and as the policies of the pandemic continue to sour, they’ll do anything but talk about it. This more than anything is the reason for the deafening silence surrounding all of these matters. What critique there is will increasingly attach itself to isolated matters, such as school closures, and to specific initiatives in which few participated directly, such as the buying of vaccines. They’ll do everything they can to assign blame in those few areas, where they can’t be blamed themselves.
This article originally appeared on Eugyppius’s Substack newsletter. You can subscribe here.
Babies in this section of the Pfizer documents sustained respiratory distress, including from air sacs leaking between lungs and chest walls. Babies and fetuses were dying.
Pfizer knew that “exposure” as they defined it, included sexual intercourse with vaccinated men, as well as skin contact and inhalation. They knew that 19 per cent of the babies identified, in the first three months of the study, sustained adverse events, many of them serious; one baby was rushed to the hospital.
Babies in this section of the Pfizer documents sustained respiratory distress, including from air sacs leaking between lungs and chest walls. Babies and fetuses were dying. My interview with Northern California longtime midwife Ellen Jasmer revealed that she is seeing a great deal of this — babies who seem fine at birth, go home, but who are rushed to hospital within a day with respiratory distress — and Pfizer knew in April 2021 — two full years ago — that this would indeed happen.
This, by the way, is the kind of abnormal, flattened, damaged placenta that Nurse-Midwife Ellen Jasmer is seeing now in her practice. She says she sees almost no normal placentas any more:
Pfizer knew perfectly well that it was harming multiple aspects of the reproductive process in women. In its secret documents the company calmly described what it called “fetal poles” with no heartbeats, and amniotic sacs without any fetuses, along with other horrors. The documents make use too of the bizarre phrase “missed abortions”.
Why would you use such a phrase in internal documents unless you are trying to elicit spontaneous abortions or miscarriages?
In addition to damage to the fetuses and babies via the moms’ injections, the new tranche of documents also reveal that the PEG in vaccinated moms’ breast milk causes horrendous damage to tiny newborns trying to nurse. We broke this story about contaminated breast milk many months ago, but this tranche of new documents adds confirmation to the fact that Pfizer knew it was poisoning vaccinated women’s breast milk.
The babies in the documents who nursed from vaccinated moms had peeling skin, blurred vision, agitation, convulsions, rashes, fevers, myalgia, vomiting, inflammation of tissues, tissue edema, and many other horrendous conditions.
The data about all of this damage to fetuses and babies were compiled by Pfizer by April 20 2021. The report went to the FDA, and from there to the CDC. Astonishingly, three days later, knowing about this shocking report tallying dead fetuses, dead babies, and babies in distress, Dr Rochelle Walensky called a major White House press conference, at which she declared that the vaccines were “safe and effective” and launched an aggressive PR campaign to urge, bully and “recommend” that pregnant “persons” receive mRNA vaccines ‘for the safety of their babies.’
Dr Walensky was guilty of these shocking lies, in her April 23 2021 press conference:
“Moving on, I want to share a new study that was published this week by CDC scientists. On Wednesday, the New England Journal of Medicine published the preliminary findings of post-COVID-19 vaccine surveillance in pregnant persons. Clinical trials of COVID-19 vaccines did not include pregnant people, leaving us with limited data on the safety of vaccination in pregnant people and babies to date.
Through county — country-wide surveillance, using the CDC v-safe app and the v-safe Pregnancy Registry, as well as the Vaccine Adverse Event sys- — Reporting System, we were able to follow over 35,000 pregnant people who were vaccinated.
Pregnant people experienced the same side effects as others following vaccination. We were also able to follow, in detail, more than 3,900 pregnant women, and over 800 of whom have completed their pregnancies.
Importantly, no safety concerns were observed for people vaccinated in the third trimester or safety concerns for their babies. [Italics mine]
I have in my book The Bodies of Others already taken apart “V-Safe” — the non-science pathetic excuse for a surveillance system for pregnant “people” – which is not in fact a double blind study in any way but is rather a phone app, staffed not by physicians or scientists, but by a call center, to which strangers you are supposed to self-report your miscarriage or spontaneous abortion — a totally normal thing to want to do when you have lost your baby.
This pathetic substitute for science, this phone app, is also designed to stop tracking women and babies right when newborn babies are going to reveal problems, if problems exist.
Dr. Walensky hid from American and the world’s women, the fact that Pfizer in its in- depth internal documents had calmly concluded that the company was murdering and injuring babies and fetuses; and she called attention, rather, to the awesome outcomes revealed, or engineered, by a thoroughly gamed phone app.
The mRNA vaccines were released globally in early 2021 with the slogan ‘safe and effective’. Unusually for a new class of medicine, they were soon recommended by public health authorities for pregnant women.
The mRNA vaccines were released globally in early 2021 with the slogan ‘safe and effective’. Unusually for a new class of medicine, they were soon recommended by public health authorities for pregnant women. By late 2021, working age women, including those who were pregnant, were being thrown out of employment for not agreeing to be injected. Those who took the mRNA vaccines did so based on trust in health authorities – the assumption being that they would not have been approved if the evidence was not absolutely clear. The role of regulatory agencies was to protect the public and, therefore, if they were approved, the drugs were safe.
Recently, a lengthy vaccine evaluation report sponsored by Pfizer and submitted to the Australian regulator, the Therapeutic Goods Administration (TGA) dated January 2021 was released under a Freedom of Information request. The report contains significant new information that had been supressed by the TGA and by Pfizer itself. Much of this relates directly to the issues of safety in pregnancy and impacts on the fertility of women of child-bearing age. The whole report is important, but four key data points stand out:
The rapid decline in antibody and T cells in monkeys following a second dose;
Biodistribution studies (previously released in 2021 through an FOI request in Japan);
Data on the impact of fertility outcomes for rats;
Data on foetal abnormalities in rats.
We focus on the last three items as, for the first point, it is enough to quote the report itself: “Antibodies and T cells in monkeys declined quickly over five weeks after the second dose of [Pfizer Covid vaccine] BNT162b2 (V9), raising concerns over long term immunity.” This point indicates that the regulators should have anticipated the rapid decline in efficacy and must have known at the outset that the initial two dose course was unlikely to confer lasting immunity and would, therefore, require multiple repeat doses. This expectation of failure was recently highlighted by Dr. Anthony Fauci, former director at the U.S. NIH.
The three remaining items should be a major cause for concern with the pharmaceutical regulatory system. The first, as revealed in 2021, involved biodistribution studies of the lipid nanoparticle carrier in rats, using a luciferase enzyme to substitute for the mRNA vaccine. The study demonstrated that the vaccine will travel throughout the body after injection and is found not only at the injection site but in all organs tested, with high concentration in the ovaries, liver, adrenal glands and spleen. Authorities who assured vaccinated people in early 2021 that the vaccine stays in the arm were, as we have known for two years, not being honest.
In terms of the impact on fertility and foetal abnormalities, the report includes a study of 44 rats and describes two main metrics, the pre-implantation loss rate and the number of abnormalities per foetus (also expressed per litter). In both cases the metrics were significantly higher for vaccinated rats than for unvaccinated rats.
Roughly speaking, the pre-implantation loss ratio compares the estimated number of fertilised ova and the ova implanted in the uterus. The table below is taken from the report itself and clearly shows the loss rate for vaccinated (BNT162b2) is more than double the unvaccinated control group.
In a case control study, a doubling of pregnancy loss in the intervention group would represent a serious safety signal. Rather than take this seriously, the authors of the report then compared the outcomes to historical data on other rat populations – 27 studies of 568 rats – and ignored the outcome because other populations had recorded higher overall losses. This range is shown in the right hand column as 2.6% to 13.8%. This analysis is alarming as remaining below the highest previously recorded pregnancy loss levels in populations elsewhere is not a safe outcome when the intervention is also associated with double the harm of the control group.
A similar pattern is observed for foetal malformations with higher abnormality rate in each of the 12 categories studied. Of the 11 categories where Pfizer confirmed the data are correct, there are only two total abnormalities in the control group, versus 28 with the mRNA vaccine (BNT162b2). In the category which Pfizer labelled as unreliable (supernumerary lumbar ribs), there were three abnormalities in the control group and 12 in the vaccinated group.
As with the increased pregnancy losses, Pfizer simply ignored the trend and compared the results with historical data from other rat populations. This is very significant as it is seen across every malformation category. The case control nature of the study design is again ignored, in order to apparently hide the negative outcomes demonstrated.
These data indicate that there is no basis for saying the vaccine is safe in pregnancy. Concentration of lipid nanoparticles in ovaries, a doubled pregnancy loss rate and raised foetal abnormality rate across all measured categories indicates that designating a safe-in-pregnancy label (B1 category in Australia) was contrary to available evidence. The data imply that not only was the Government’s ‘safe and effective’ sloganeering not accurate, it was totally misleading with respect to the safety data available.
Despite the negative nature of these outcomes, the classification of this medicine as a ‘vaccine’ appears to have precluded further animal trials. Historically, new medicines, especially in classes never used in humans before, would require a very rigorous assessment. Vaccines, however, have a lower burden of proof requirement than ordinary medicines. By classifying mRNA injections as ‘vaccines’, this ensured regulatory approval with significantly less stringent safety requirements, as the TGA itself notes. In fact, these mRNA gene therapy products (to use the proper term) function more like medicines than vaccines in that they modify the internal functioning of cells, rather than stimulating an immune response to presence of an antigen. Labelling these gene therapy products as ‘vaccines’ means that, as far as we are aware, even today no genotoxicity or carcinogenicity studies have been carried out.
This report, which was only released after a FOI request, is extremely disturbing as it shows that authorities knew of major risks with mRNA COVID-19 vaccination while simultaneously assuring populations that it was safe. The fact that mainstream media have (as far as we are aware) completely ignored the newly released data should reinforce the need for caution when listening to the advice of public health messaging regarding COVID-19 vaccination.
Firstly, it is clear that regulators, drug companies and the Government would have known that vaccine induced immunity tails off very rapidly, with this being subsequently observed in real world data with efficacy against infection falling to zero. Accordingly, the single point in time figures of 95% and 62% efficacy against symptomatic PCR-positive infection quoted for Pfizer and AstraZeneca respectively meant almost nothing since a rapid decline was to be expected. Similarly, the concept of a two dose course was inaccurate as endless boosters would likely have been required given the rapid decline in antibodies and T-cells observed in the monkeys.
Most importantly, the data do not in any way support the ‘safe’ conclusion with respect to pregnancy; ‘dangerous’ would be much more accurate. The assurances of safety were, therefore, completely misleading given the data disclosures in the recent freedom of information release. Regulatory authorities knew that animal studies showed major red flags regarding both pregnancy loss and foetal abnormalities, consistent with the systemic distribution of the mRNA they had been hiding from the public. Even in March 2023, it is impossible to give these assurances, given the fact that important studies have not, to the best of our knowledge, been done. Pfizer elected not to follow up the vast majority of pregnancies in the original human trials, despite high miscarriage rates in the minority they did follow. Given all of the problems with efficacy and safety, the administration of these products to women of childbearing age and administration to healthy pregnant women is high risk and not justified.
Alex Kriel is by training a physicist and was one of the first people to highlight the flawed nature of the Imperial Covid model; he is a founder of the Thinking Coalition which comprises a group of citizens who are concerned about Government overreach. David Bell is a public health physician with a PhD in population health and formerly worked as a scientific and medical officer at the World Health Organisation.





You must be logged in to post a comment.